Skip to content
Rafter
PlatformHow it worksSecurityFAQFor ACOsFree tools
Sign inGet my free look-backFree look-back

Your last 30 days are hiding a number. Want to see it?

Built for independent practices · 1–15 clinicians

Your sickest patients look healthy on paper. That’s why you’re underpaid.

Every chronic condition you treat but don’t document to standard makes your panel look healthier than it is — and, by industry benchmarks, costs a small practice tens of thousands a year in Medicare Advantage revenue and denied claims. Rafter finds those gaps with AI before the visit, so the chart finally shows the work you already do.

Get my free look-backBook a 15-minute fit call

Free · No commitment · Your charts, your number — in about 15 minutes

In an ACO? See how Rafter works for ACO practices →

  • HIPAA-compliant under a BAA
  • PHI de-identified before AI ever sees it
  • Runs on athenahealth & eClinicalWorks — no EHR change
  • Physicians never see dollars — by construction
Look-Back ReportSample report · 30-day window, annualized
Missed, recoverable diagnoses$138,910 found
Documented but at audit risk (no MEAT evidence)$123,337 exposed
CKD stage 3b — eGFR 38 in labs, never on the claimRecapture
On insulin + SGLT2 — diabetes complication undocumentedHigh confidence
Heart failure coded — no MEAT evidence in the noteAt audit risk

Illustrative example. Your report is built from your charts — de-identified before any AI processing, under a signed BAA. See the full sample report →

Whose side is your gap tool on?

Your health plan’s gap reports work for the plan — one payer at a time, from claims, after the visit. Rafter works for your practice: every payer, before the visit, with documentation built to hold up in an audit. No new system to learn, no staff to add.

In an ACO? Rafter works alongside it.

Your ACO’s tools are built for its contract. We cover what they leave to you: visit coding, your Medicare Advantage and commercial patients, payer rules and claims. One flat price per clinician, with no share of your savings.

Learn more

The problem

Every practice has two leaks. Most tools only talk about one.

1Money you never capture

Conditions you’re actively treating — the CKD sitting in the labs, the diabetes complication behind the insulin — never make it onto a claim. On Medicare Advantage panels that’s real revenue, and it resets to zero every January 1st.

2Money you capture but can’t keep

Diagnoses that are coded but not documented to MEAT standard get denied now — or clawed back in a RADV audit years later. Regulators collected nine-figure settlements in 2026 for exactly this.

77%
of providers report rising claim denials — industry surveys.
~$3,000/yr
per member lost to documentation gaps — industry benchmark.
Jan 1
every undocumented chronic condition resets and must be recaptured — CMS-HCC rules.

Rafter works both leaks at once: capture what’s real, defend what’s documented — and prove it with evidence.

Get my free look-back

What Rafter does

Find it. Document it. Defend it. Get paid.

One HIPAA-compliant platform that reads the chart the way an auditor would — before the visit, not after the denial.

Pre-visit HCC gap detection

Days before each appointment, AI cross-checks meds, labs, and history against what’s actually documented — and hands your physician the short list while the patient is still in the room. CMS-HCC V28, built for Medicare Advantage panels.

Audit-proof what you capture

Every diagnosis is checked against MEAT evidence before it ships. What doesn’t hold up gets flagged — so you’re never the practice explaining itself in a RADV audit.

Denials prevented, not appealed

Coverage, medical necessity, and coding issues get caught before the claim leaves the building. When one slips through, the appeal drafts itself from the chart.

Coding that keeps up with the clinic

Notes become accurate ICD-10 and E/M codes automatically, with a human confirming the judgment calls — your coder’s best day, every day.

Three taps, between patients

Physician queries are written to be answered in under 30 seconds on a tablet. No codes, no dollar figures, no homework — just a clinical question. Doctors never see the financial side. Ever.

Your staff or ours

Have a coder? Rafter makes them faster. Don’t? A Rafter billing-and-coding specialist runs it end to end. Short-staffed isn’t a blocker — it’s who we built this for.

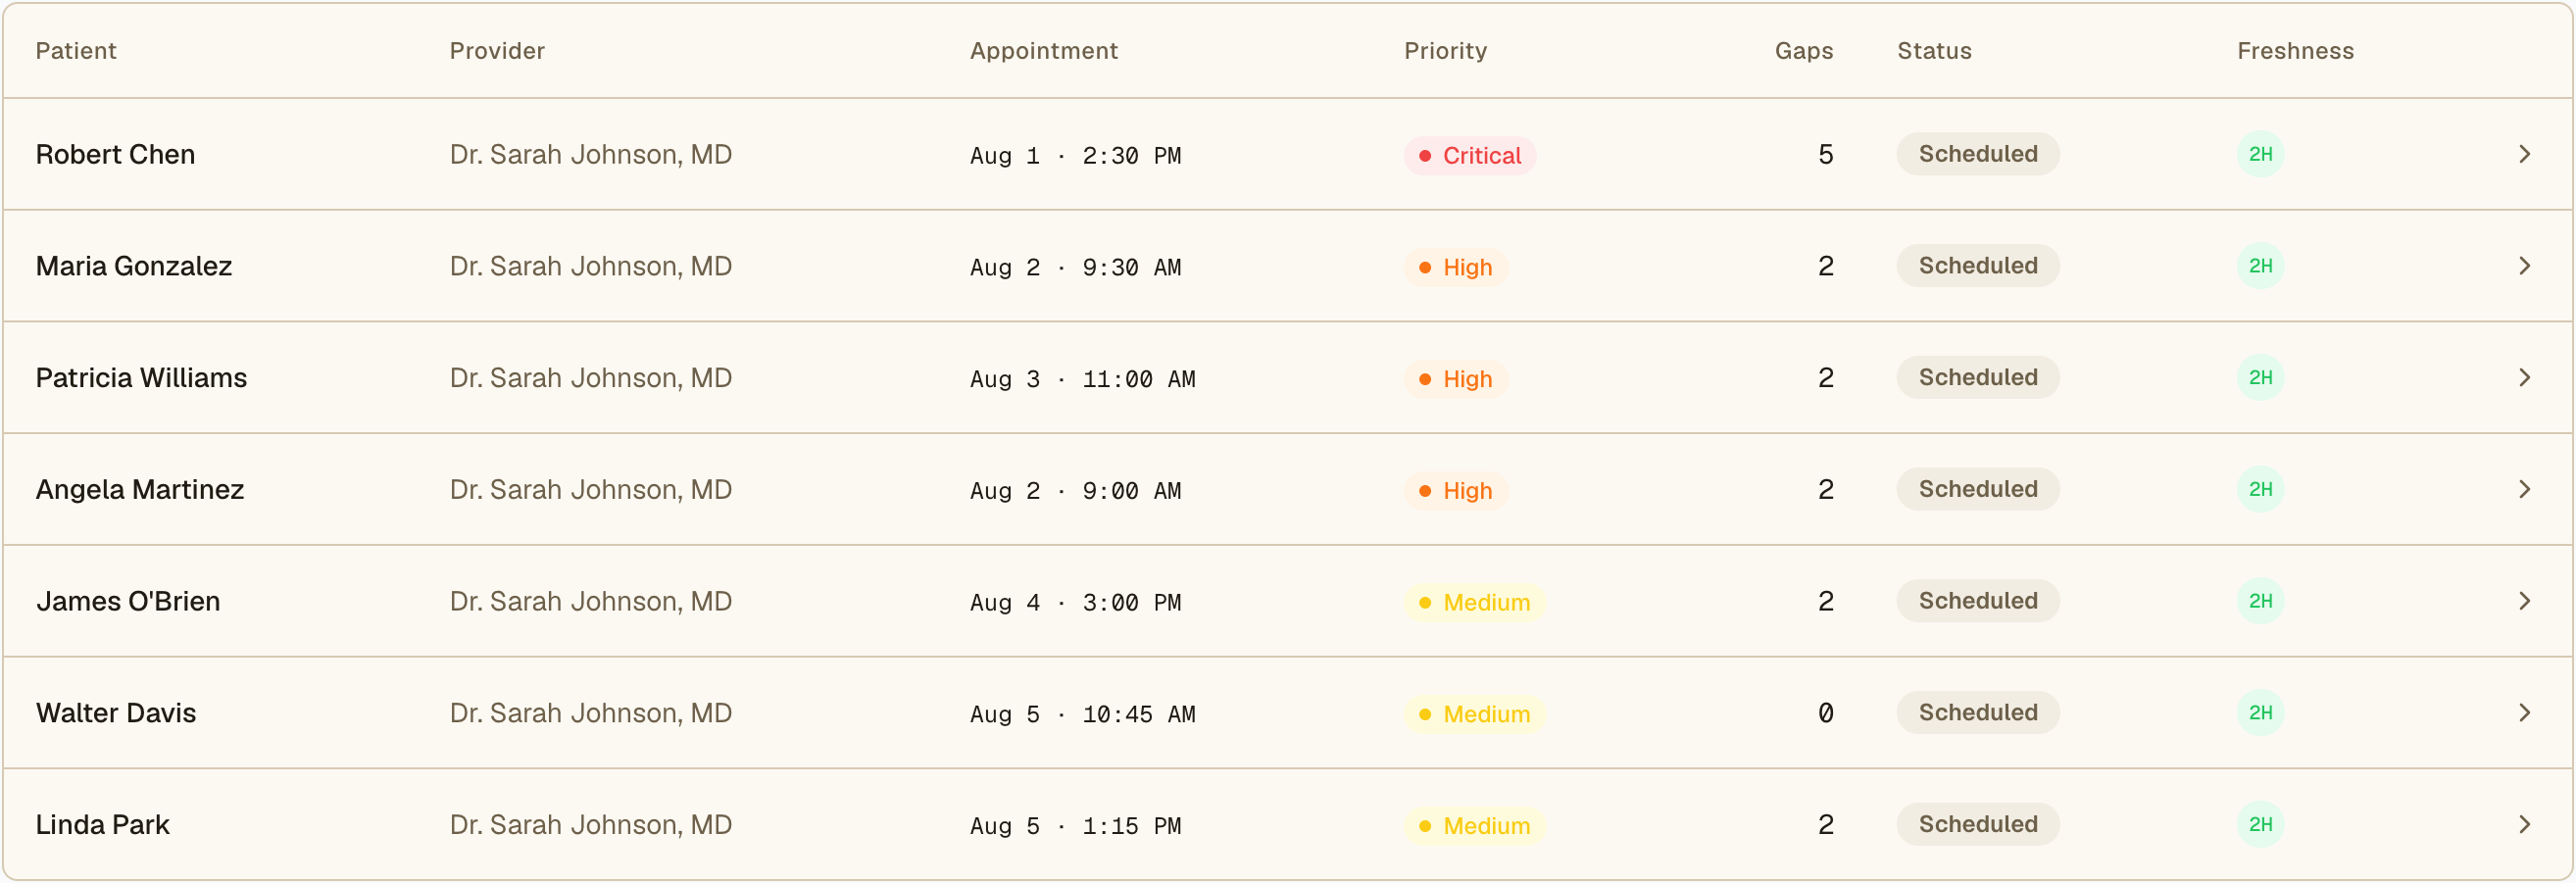
Rafter pre-visit planning queue listing seven upcoming Medicare Advantage appointments, each with provider, appointment time, priority, documentation-gap count, status, and data freshness
The pre-visit planning queue — every upcoming Medicare Advantage visit reviewed days ahead, prioritized by documentation gaps. De-identified demo data.

How it works

Live in days, not a quarter.

1

Connect your EHR — about 15 minutes

A secure FHIR connection to athenahealth or eClinicalWorks, covered by a signed BAA. Your workflows don’t change. Nothing is ripped out or replaced.

2

Rafter reads ahead

Every upcoming visit is scanned for undocumented conditions, missing evidence, and denial risk. Patient data is de-identified under HIPAA Safe Harbor before any AI model touches it — by default, not by setting.

3

Your team acts, the claim goes out clean

Physicians answer 3-tap queries; your coder (or ours) confirms; the claim leaves the building already documented, coded, and defensible — with a 10-year audit trail behind it.

No new software for physicians to learn. No IT project. No enterprise contract.

See it on your own charts

Free tools

Check our data before you trust our pitch.

Four free lookups running on the same licensed CMS dataset the Rafter engine validates against. No login. No email gate. Bookmark them, share them with your coder.

HCC V28 Explorer

Any ICD-10 code → its V28 category and PY2026 RAF weights, all seven segments.

Open free →

RAF Calculator

Paste a problem list. Hierarchies applied, coefficients summed — the condition RAF.

Open free →

CC/MCC Checker

Base and effective status — with the CMS exclusion pairs static lists miss.

Open free →

MS-DRG Lookup

FY2026 weights, GMLOS, and the severity split one documented MCC changes.

Open free →

Refreshed every October 1 when CMS updates the fiscal year. Explore all free tools →

Risk-free

See your number. Then decide.

Pick either path — both start with one 15-minute call, and neither costs you anything.

Most popular

The 30-day look-back

We run a previous 30-day period of your charts through the engine — under a signed BAA, fully HIPAA-compliant — and hand you a report showing, in dollars, the diagnoses that slipped through and the documented ones that wouldn’t survive an audit.

Your charts. Your number. No commitment.

The risk-free 30-day trial

Turn Rafter on for your upcoming visits and watch it work in your live workflow for a month — pre-visit gap flags, 3-tap physician queries, clean claims out the door.

If it doesn’t earn its keep, walk away.

If the number isn’t worth a meeting, delete our email. But it usually is.

And when you’re ready, there are two ways to pay. In an ACO? One flat price per clinician, with no share of your savings. Not in an ACO? Pay only out of new, defensible revenue we help you capture: if we don’t find it, you don’t pay. No six-figure contracts. No percent-of-everything tax.

Get my free look-backBook a 15-minute fit call

Security and compliance

Compliance isn’t a feature. It’s the default state.

  • HIPAA-compliant under a signed BAA. Before any chart moves, the paperwork is in place.
  • PHI never reaches an AI model un-scrubbed. HIPAA Safe-Harbor de-identification runs first — on by default, hard-fails if it can’t.
  • Documents never leave the building. OCR runs locally — not in someone else’s cloud.
  • Physicians never see dollars. Queries are clinical questions only; the financial engine is firewalled to admin views. That’s AHIMA/ACDIS-compliant by construction — and it’s why “is this upcoding?” has a clean answer: no.
  • Ten-year audit trail. Every query, response, and code decision is logged to CMS RADV retention standards.

Bring your compliance officer to the call. We like those meetings.

PHI de-identificationOn by default
Local document OCROn by default
MFA + role-based accessEnforced
Audit logging (10-yr RADV)On
SOC 2 Type IIIn progress

Questions we always get

Asked by every practice. Answered straight.

Is this upcoding?+

No — and the architecture makes it impossible to drift there. Rafter only surfaces conditions with clinical evidence in the chart, every query lets the physician say “not present,” at-risk codes get removed, and doctors never see financial data. Accuracy cuts both ways; that’s what makes it defensible.

Do we have to change our EHR?+

No. Rafter connects to athenahealth and eClinicalWorks over FHIR and works alongside them. Your notes, your templates, your billing flow — untouched.

Our health plan already sends us gap reports.+

Good — keep them. Those are claims-derived and cover that plan’s members only, and they tell you what’s missing, not whether your note would survive the audit. We work your whole panel, before the visit, and make each condition MEAT-defensible.

We’re in an ACO, and they already show us gaps.+

Your ACO’s app is great at telling you which patients matter for your contract. We make the documentation on those visits complete and defensible: MEAT evidence, compliant queries, accurate E/M. That protects the benchmark your ACO is measured against. Rafter works alongside your ACO, not instead of it, at a flat price per clinician with no share of your savings.

How Rafter works for ACO practices →

How do you price for ACO practices?+

One flat monthly price per clinician that covers every payer. It doesn’t change with what we find, and a clinician who bills fewer than 150 visits in a month is half price.

See the ACO plans →

Do you take a share of our shared savings?+

No. Your ACO shares savings with you, and we stay out of that. Our price isn’t tied to diagnoses, risk scores or collections.

Our scribe handles documentation.+

Scribes capture what was said — brilliantly. They can’t flag what was never said. We scan the chart before the visit so the conditions being treated actually get addressed and documented. Keep the scribe; we plug in on top.

We don’t have staff to run another tool.+

Then don’t — a Rafter billing-and-coding specialist can run coding and claims for you. If you do have staff, Rafter just makes their queue shorter. Either way, physicians only ever see 3-tap questions.

How is patient data protected?+

HIPAA-compliant end to end: signed BAA before any data moves, PHI de-identified under Safe Harbor before any AI processing, local OCR, role-based access, MFA, and a 10-year audit log. Happy to walk your compliance officer through it on the call.

Mostly Traditional Medicare in an ACO: is this still worth it?+

Yes. On Traditional Medicare, HCCs pay nothing directly, so we don’t price them. The money is in the visit: E/M level, G2211, clean claims, fewer denials. HCC findings on those patients are counted, and complete documentation protects the benchmark your ACO is measured against.

See what an ACO practice gets →

No risk contract at all — is this still worth it?+

Yes, differently. The RAF revenue story is strongest in Medicare Advantage; pure fee-for-service practices see the value in cleaner coding, fewer denials, and faster payment. The 15-minute call sorts out which story is yours.

What does it cost?+

The look-back is free. After that there are two ways to pay. In an ACO? A flat price per clinician, with no share of your savings and no fee tied to HCCs. Not in an ACO? A performance plan: we’re paid a share of new, defensible revenue we help capture, so if we don’t find anything, you don’t pay. Exact numbers get built on the call, not guessed at on a website.

See the ACO plans →
Get started

Thirty days of charts. One 15-minute call. Your number, in dollars.

Tell us a little about the practice and we’ll come prepared — you bring nothing. We’ll answer the compliance questions and set up your free look-back if you want it.

  • 15–20 minutes, on your calendar, with a specialist — not a script-reader
  • See the look-back process on an athenahealth / eClinicalWorks setup like yours
  • Leave with a clear yes/no on whether your practice is a fit — either answer is fine

Book your call — and we’ll set up your free look-back

We reply within 4 business hours on weekdays with times.

Fastest way to lock in a time.

athenahealth and eClinicalWorks connect same-week.

No spam, no obligation, no pressure — one call, then you decide. Please don’t include any patient information (PHI) in this form. Once we work together, everything runs HIPAA-compliant under a signed BAA.

Risk-free · HIPAA-compliant · No EHR change

The revenue is already in your charts. Let’s go find it.

Get my free look-back

Already a customer? Sign in →

Rafter

The revenue-integrity command center for independent practices — 1 to 15 clinicians.

Austin & Central Texas

Platform

HCC gap detectionAudit defenseDenial preventionAutomated coding

Free tools

HCC V28 ExplorerRAF CalculatorCC/MCC CheckerMS-DRG Lookup

Get started

Book a callFree look-backFor ACO practicesSign in

Trust

SecurityHIPAA & BAAContact
© 2026 Rafter · Rafter is a product of THS Enterprise Technologies LLCHIPAA-compliant under a BAA · PHI de-identified before any AI processing · 10-year RADV audit retention

Statistics shown are industry figures, not guarantees of results.